


- 91% of office-based providers use a certified EHR (2024 data)
- EMRs stay within one practice; EHRs share records securely across providers
- 70% of healthcare professionals say their team corrects missing or delayed lab results
- Providers spend 4.8 hours a week charting outside scheduled hours
- Practices spend an average of 13 hours a week on intake paperwork
- 17% of patients say they’d switch providers if they can’t book online
TL;DR
Choose an EHR by mapping your patient journey, confirming certification, and making vendors demo your hardest workflow — 63% of providers want one login and unified tools, and most adoption problems surface in weeks 2 to 6 after go-live, so plan for that stretch before you sign. Tebra’s cloud-based, certified EHR connects charting, billing, and scheduling for private practices.
EHR systems in healthcare are now standard, and their usage has increased from 42% in 2008 to 95% in 2024.
Many practice owners even call it a practice’s “central nervous system,” and for good reason.
Every time a patient visits your practice, the EHR stores all the information about the visit and any follow-up plans. By the time they’re done and reach their car, the claim for the visit can be generated and on its way to the payer — that is, if the EHR works well.
In this guide, we’ll explain what an EHR is, how it differs from other healthcare systems, and what to look for when you’re buying one for your practice.
What is an electronic health record (EHR)?
An electronic health record (EHR) is a real-time, digital version of a patient’s chart. It securely stores demographics, diagnoses, medications, allergies, test results and clinical notes, and it gives you and other authorized providers instant access to a patient’s full medical history.
The difference between an EHR and a paper-based chart is that the former is built for secure sharing. Paper-based records are prone to damage, data loss or unauthorized sharing.
With an EHR, you can avoid these issues by securing everything digitally and putting the right controls in place to prevent data loss or leaks.
As of 2024, 99% of hospitals and 91% of office-based providers use a certified EHR. And this change has been accelerated through the introduction of regulations like the HITECH Act (2009) and Health IT modules in the Health IT certification program (2010). That said, solo practice providers are still playing catch up, likely because it’s too expensive or complex to implement.
| An electronic health record is a digital system that securely stores and organizes a patient's essential health information, providing a comprehensive view of their overall health. |
What information is included in an EHR chart?
A typical EHR chart includes the clinical details a provider needs to make decisions, plus any administrative details that apply. For example:
- Identity and coverage: Name, date of birth, contact details, emergency contacts and insurance information
- Medical history: Past diagnoses, surgeries, immunizations, family history and habits like smoking or alcohol use
- Medications and allergies: Current and past prescriptions, dosages and recorded reactions
- Results and vitals: Lab work, imaging and pathology reports, and readings like blood pressure, heart rate and weight over time
- Encounters and care plans: Progress notes, diagnoses, referrals, orders and treatment plans from each provider involved
- Patient-reported and social data: Symptom or quality-of-life questionnaires, social determinants of health (SDOH) and genomic data in some specialties
Note: With Tebra’s cloud-based EHR, you see this view on one screen, with lab orders and billing details for each visit close at hand.

The differences between EHR vs EMR vs PHR
Even though these acronyms sound like they refer to the same system, they don’t. The difference comes from who manages the record and how far it can travel after it leaves your examination room. Here’s what that means:
- Electronic medical record (EMR): A digital chart that stays within a single practice, used mostly for that practice’s documentation and billing.
- Electronic health record (EHR): A record designed to travel with the patient and be shared securely with other providers and labs involved in their care.
- Personal health record (PHR): A PHR is a record that the patient owns and manages. It’s usually built from information the patient downloads from their providers or adds themselves.
| EMR | EHR | PHR | |
| Who manages it | One practice | Providers across organizations | The patient |
| What it covers | Visits at that practice | Full history across providers | Whatever the patient adds or imports |
| Shared with other providers | Rarely | Yes, securely | When the patient chooses |
| Typical example | A standalone charting system in one clinic | A certified EHR connected to labs, pharmacies, and health information exchanges | A health app or a file of downloaded records |
| Federal certification | Varies | ONC certification available | Not certified |
The best-case scenario is using an EHR because it keeps a complete record of your patient, and that “file” updates every time they visit you or another provider.
Pro tip: Many vendors use EMR and EHR interchangeably, so ask whether they can share the record securely. If you’d still like to understand the differences, check out our guide on EMRs vs. EHRs.
What are the core capabilities of EHR systems in healthcare?
Every EHR should have two sets of capabilities: clinical and administrative. Here’s a list of features each of them should include:

Clinical tools
You and your clinical staff use these tools while you treat patients and document their care:
Charting templates and AI notes
Charting tools are how you document each visit. In Tebra’s 2026 after-hours charting report, providers spent an average of 4.8 hours a week charting outside scheduled hours. It’s time-consuming, so look for specialty-specific templates and an AI tool that drafts notes from your conversations.
ePrescribing (eRx)
ePrescribing lets you send a prescription directly from the patient’s chart to their pharmacy. Because it starts in the chart, your EHR can check it against the patient’s medication and allergy list before sending it out.
Tip: For controlled substances, you’ll need electronic prescribing of controlled substances (EPCS) and a built-in check against your state’s prescription drug monitoring program (PDMP).
eLabs
eLabs connect your EHR to the labs you work with. When you order a test from the chart, the results come back right there. Seventy percent of healthcare professionals say their team has to correct missing or delayed results, and 74% say this affects a diagnosis or treatment decision. To avoid this, check if the EHR has an eLabs module to send and receive this data.
Clinical decision support
Clinical decision support (CDS) includes the alerts and reminders your EHR shows you during a visit. The suggestions are usually based on the patient’s chart and evidence-based guidelines. For example, a CDS can flag a drug-allergy conflict as you prescribe medication.
Patient portal and secure messaging
The patient portal is a secure website or app where patients can view visit summaries and test results and message your team. It replaces phone calls with text-based messaging. As of 2026, 56% of providers already follow up with patients through a portal — so it’s now a necessity as more patients expect fluid communication.
Telehealth
An EHR with a built-in HIPAA-compliant telehealth module lets you run video visits from the same schedule and chart you use for in-person appointments.
Erika Joy Puruleski, MSN, APRN, PMHNP-BC, of Joy Integrative Psychiatry, runs a solo, 100% telehealth psychiatry practice in Peoria, Arizona. With no front desk or IT team to cover for disconnected tools, she depends on everything living in one place. “I refuse to give up the patient portal with online intake paperwork, built-in telehealth, and note templates. Having intake forms done before the first visit means the appointment is spent with the patient, not on paperwork,” she says.
Administrative tools
These tools help you run the business side of each patient visit:
Digital intake
Digital intake lets patients complete their forms online before the visit, and their answers flow straight into the chart. Practices spend an average of 13 hours a week on handling intake paperwork. Choose a system that automatically connects intake answers to the patient record.
Online scheduling and reminders
Online scheduling lets patients book and reschedule appointments themselves. Plus, the EHR sends automated reminders by text or email before each visit. This matters because 17% of patients say they’d switch providers if they can’t book online. And 69% say they’re more likely to show if they can reschedule online.
Billing and medical coding
If your EHR integrates billing, you can suggest the right diagnosis and treatment codes. And you can send this information into the claims submission form directly. This reduces the chance of coding errors and claim denials.
Reporting and quality programs
With the number of patient records and workflows you’ll have, it’s important to understand how the practice functions as a whole. Reporting tools help by consolidating data from revenue to quality measures.
If you participate in Medicare’s Merit-based Incentive Payment System (MIPS), your EHR data also determines whether you earn a positive or negative payment adjustment.
Role-based access controls
HIPAA’s minimum necessary standards require you to limit access to information based on a person’s role and job needs. Use role-based access to decide which staff members can access specific types of data and who can edit them.
Your EHR should also keep a record of who opens each record and when — in an audit log.
EHR based on medical specialty
In our conversations with practice owners, we also found they choose EHRs based on whether they were purpose-built for them. For example, Dr. Masoud Saman, a double board-certified plastic surgeon, says that in dermatology practices, documentation like photos of burns or lesions really matters because words can’t capture the gravity of the wound.
Similarly, functional medicine practices like Advanced Natural Health Center need telehealth-specific features. This is because it doesn’t have a physical office, and patients need secure remote access to their records, so it’s non-negotiable.
So consider your specialty type too when researching an EHR.
What are the benefits of using an EHR?
The main goal of using an EHR is to stop information from getting lost between people or practices. Here’s how that effort impacts your practice:
- Better care coordination: Every member of your team can see the same up-to-date chart at the same time, and everything updates in real time. For instance, providers like Dr. Mikel Daniels have used an EHR in his podiatry and wound care practice since 2007. One of the first changes he noticed was better access to information. “I started using an EHR in 2007, and we stopped misplacing charts, and I was able to see a patient’s chart without having to be in the office,” he says.
- Fewer medication errors: In a 2026 Tebra survey, 18% of practices said intake errors had led to an adverse clinical event — like wrong medication or an allergic reaction. Most EHRs default to checking a patient’s prescription against specific allergies or current medications to reduce the risk of adverse interactions. As a result, you can reduce medical errors caused by handwritten, illegible scripts or an incomplete medication list.
- Less time on documentation: Most modern EHRs offer two features that reduce documentation time: specialty-specific templates and AI-assisted note-taking. Templates keep you from having to create your own or tweak existing ones to fit your practice’s needs, while AI-assisted notes transcribe patient conversations and summarize them. In fact, Noah Gula, AVP at OSP in Florida, has helped an orthopedic group move to Tebra and describes the solution this way: “Providers used to carry unfinished notes into the evening or next day. With better templates and workflows, they completed far more documentation before leaving. The gain was less work spilling into the evenings.”
- Cleaner billing processes: When you use an EHR with built-in claims processing, it ensures claims are created from the chart and mapped to the right billing codes. If there are errors, it also scrubs the claims to reduce the number of denials your team has to fix in the future.
- Easier access for patients: A Tebra survey reported that 69% of patients use AI to get a second opinion after meeting a healthcare provider. Common tools include ChatGPT and Google Gemini. But if your EHR includes built-in AI features, patients can check their results and even interpret them through approved AI channels. Plus, EHRs with two-way text messaging help patients get support faster, keeping them engaged in their own care between visits.
Tip: Use our EHR cost calculator to see how much you can save if you adopt or switch EHRs.
What are the most common challenges of EHR adoption?
Every software you try to adopt and implement comes with its own set of challenges. Some are technical, while others are sociotechnical. The EHR is no different.
Here are some common challenges of EHR adoption providers have experienced in the past:
- Increased screen time in the exam room: Patients prefer in-person visits because they get 1:1 attention from their providers. If you’re using an EHR, you might spend too much time looking at a screen instead of them, and patients notice. In fact, 49% of patients said they trust their providers’ judgment less when they’re distracted by a screen and 17% have switched or considered switching for this reason.
- Partial EHR adoption: An EHR isn’t a magic bullet, so some clinicians keep paper for one-off tasks an EHR may not capture. But it also means the EHR becomes an incomplete record if it isn’t updated. Providers like Dr. Cameron Rokhsar, who runs a dermatology and cosmetic laser practice in New York, says it’s one of the most common problems he sees. “Physicians keep paper habits for the awkward parts, such as procedure notes or consents, and the chart splits into two systems. The problem tends to surface when the first audit, records request, or complication needs a complete record,” he says.
- Sticking to old habits: Old habits die hard, so new users tend to recreate their old workflows in the EHR. Dr. Daniel’s practice has brought in several smaller practices into the group over the years and has seen this play out every time. Basically, providers try to fit a square-peg way of doing things into a brand-new hole, and it doesn’t always work out.
- The transition period takes too long: When you “go-live,” it just means that the EHR system is in place and your team gets started with it. Most people incorrectly assume that that’s the end of it. Dr. Masoud Saman, a facial plastic surgeon, describes this in practice. “In the first week everyone is careful, and the schedule is usually lightened, so the system looks like it is working. The problem tends to show up around weeks two to three, once the clinic is back to full volume. Staff are still slow in the new system, notes get started and left unfinished, and people quietly drift back to old habits to keep up," he says.
That said, you can plan for these issues before you sign the contract. And it usually comes down to setting realistic expectations and training your staff.
What are the types of electronic health records software?
You can categorize EHRs in two ways:
- By the care setting they’re built for
- By where the software is hosted
Here’s how they work:
Types of EHRs by care setting
This categorization looks at where your patients receive care, or rather, what type of system it is:
- Inpatient EHRs are built for hospitals. They support round-the-clock care across many departments, including medication administration on the floor and bed management.
- Ambulatory (outpatient) EHRs are built for clinics and private practices. They focus on scheduling, specialty templates, ePrescribing, charting, patient communication, and billing for office visits. If you run an private practice, this is the category you’ll be shopping in.
Types of EHRs by hosting model
This categorization type looks at where the EHR software is hosted:

1. Cloud-based EHRs
Cloud-based EHRs, also known as software as a service (SaaS) solutions, allow practices to access the system through the internet. These systems eliminate the need for on-site servers and infrastructure, offering a lower-cost entry point, simplified maintenance, and enhanced interoperability for seamless data sharing across networks.
Best for: Smaller, private practices or those with limited IT resources that want low upfront costs and scalability.
2. On-premise EHR software
While less common now, some healthcare organizations still use on-premise EHRs, particularly larger hospitals or health systems with specific security or customization requirements. However, even traditional on-premise vendors increasingly offer cloud options.
On-premise EHRs require you to install the software on your practice’s local servers. This model demands an upfront investment in hardware and ongoing management of local infrastructure but eliminates recurring subscription fees. However, on-premise systems also provide greater control over data storage and security.
Best for: Large practices with robust IT support that want more control over data and the ability to customize clinical content.
3. Hybrid EHR systems
Hybrid EHRs blend cloud-based and on-premise features. Data can be stored locally and in the cloud, balancing flexibility, control, and scalability. While this model supports greater customization, it requires ongoing IT management and integration of both environments.
Best for: Practices needing customizable solutions with flexibility, combining local control with cloud-based features like patient portals.
| Cloud-based | On-premises | Hybrid | |
| Upfront cost | Low (subscription) | High (servers and licenses) | Medium |
| Who maintains it | The vendor | Your practice or IT contractor | Both |
| How you access it | Any device with an internet connection | Your office network, with remote access if you set it up | A mix of both |
| Who’s responsible during an outage | Your internet provider and the vendor | Your hardware, power, and backups | Both |
| Best for | Small and private practices | Large groups with in-house IT | Practices that want local control plus cloud features |
How does an EHR system work in healthcare organizations?
Typically, 5 steps happen from before a patient enters your practice to after they leave. An EHR should cover these steps, so your team doesn’t spend too much time on data entry or duplication.
Even though the exact order varies by specialty, a typical outpatient visit follows these steps. Let’s assume you have a patient named Maria who’s 50 years old and has come in for a diabetes follow-up visit:
- Step 1. Scheduling, intake, and check-in: Maria books her follow-up online and fills out her intake forms on her phone the night before. Your front desk confirms her insurance eligibility through the EHR before she arrives.
- Step 2. Chart review and documentation: You check her A1C trend and allergy list before you walk in. Then, you document the visit with a diabetes template or an AI-drafted note.
- Step 3. Orders, ePrescribing and labs: Let’s say Maria mentions a sinus infection and you prescribe amoxicillin. When you start to prescribe amoxicillin, your EHR flags her penicillin allergy before the prescription leaves the chart. You switch to an antibiotic she can safely take and order her lipid panel from the same screen.
- Step 4. Coding, billing and checkout: Your note supports the visit codes, so the claim goes out from the same system. Maria pays her copay before she leaves.
- Step 5. Follow-up and patient access: A few days later, her lipid results land in the portal with a short note from you. Three months on, an automated reminder prompts her to book her next A1C check.
In Tebra’s 2026 lab delay index, 56% of patients assumed their provider already had their lab results when the provider didn’t. When your EHR includes this information directly in the portal, it closes the loop and clarifies next steps.
What regulations must an EHR comply with?
Before you trust an EHR to host your patient data, check whether it’s ONC-certified. An ONC-certified EHR has passed federal testing for core functions like data exchange and patient access to records. The Office of the National Coordinator for Health Information Technology runs the certification program, and it now sits within the Assistant Secretary for Technology Policy (ASTP/ONC).
This is important because it ties back to your revenue. Medicare programs like the Merit-based Incentive Payment System (MIPS) require you to handle data through certified EHR technology.
You also need to ensure the EHR complies with the Health Insurance Portability and Accountability Act (HIPAA). While ONC is focused on the software, HIPAA governs how data moves through it and how your practice uses health data.
On that note, review the EHR’s documentation and see how it works on interoperability. Your EHR should be able to send data without requiring retyping. But that’s not often the reality.
“I cannot point to a time when another practice’s records simply arrived in our chart. Fax is still very real in my office. We receive a large number of referrals and medical clearances by e-fax. A patient preparing for surgery needs a clearance from another physician, and someone on my team then has to attach that e-fax to the right chart. Every one of those is a moment when the record should have landed in our system by itself, and it happens every week,” says Dr. Saman.
Ideally, your EHR should let you scan and upload paper documents for easy access.
A note on AI: Under the HTI-1 rule, finalized in late 2023, certified EHRs that offer AI or predictive decision-making tools have to show users source information about those tools. For example, the data behind the decisions and their intended use. In December 2025, ASTP/ONC proposed a rule, HTI-5, that would remove the Predictive DSI source-attribute/model-card requirements and related risk-management requirements from certification.
How are next-generation EHRs using AI?
If you’ve ever finished a full day of appointments and then opened your laptop to a list of unsigned notes, you’ve probably already guessed where AI made its mark first.
In EHRs, AI integration started with notes and charting. In a Tebra survey, 88% of providers said that repetitive documentation is their biggest time-waster. So the first wave of AI tools went straight at this problem. AI scribes listen to the patient visit and draft notes. Once you review and approve, you sign it.
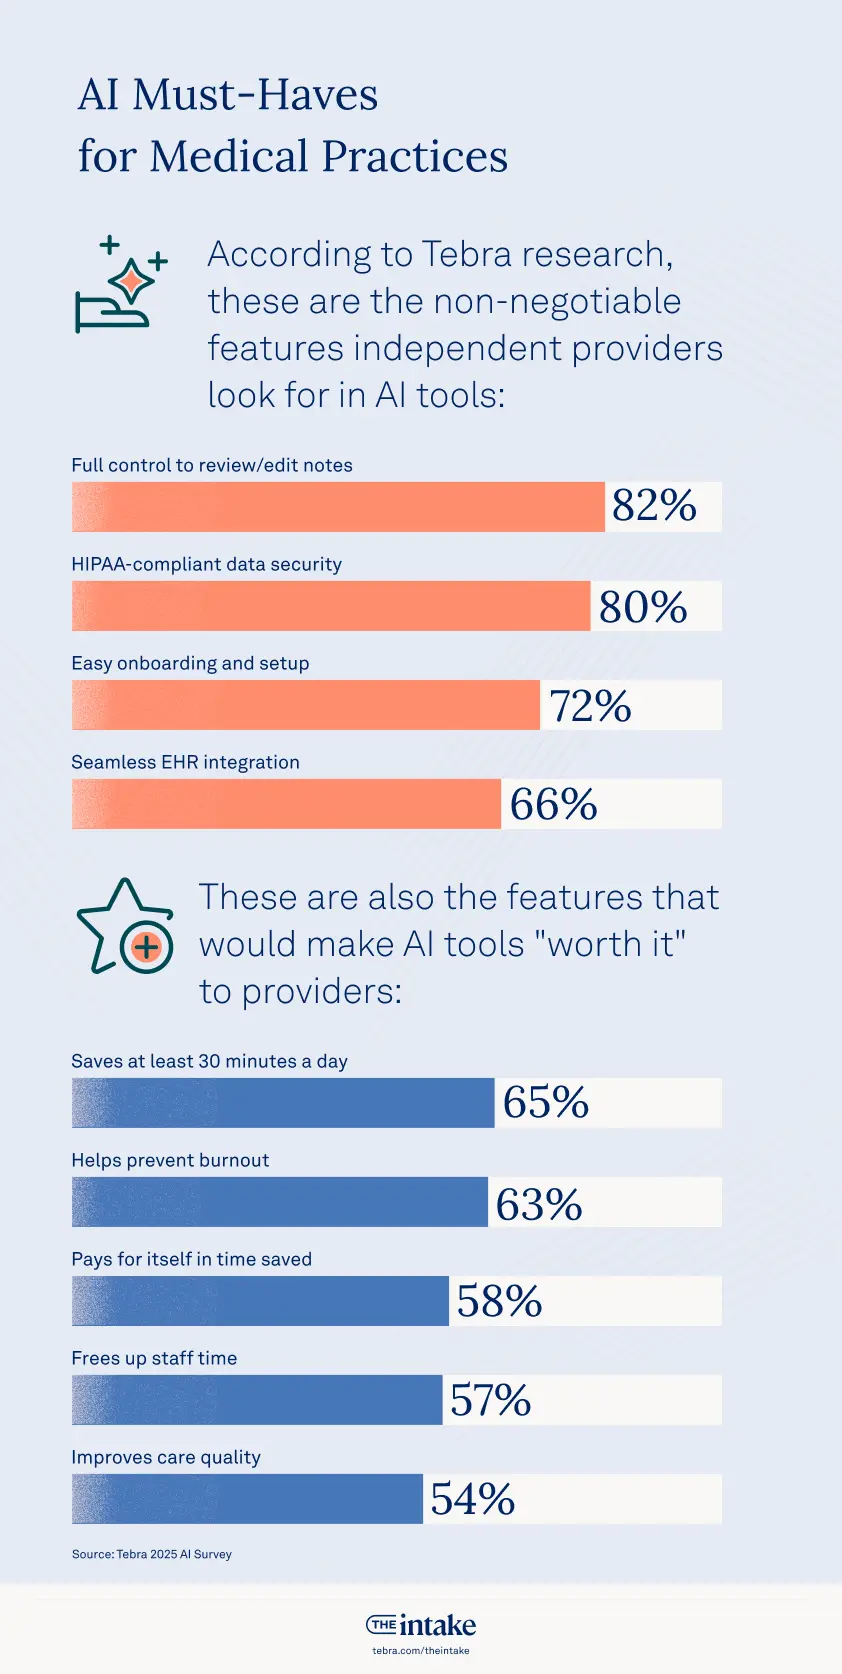
And providers have picked up these tools quickly. The American Medical Association’s survey found that 81% of physicians use AI professionally. Other than AI scribes, here are a few other ways EHRs integrate AI:
- Using an AI billing assistant to catch claim errors before claims get submitted.
- Drafting HIPAA-compliant replies for patient reviews using AI.
- Using voice assistants to answer phone calls and route complex queries to humans.
- Tracking patient sentiment by analyzing patient reviews and surfacing specific positive/negative themes.
How can you choose the right EHR for a private practice?
Here’s what practice owners and EHR implementation leads who’ve been through the process recommend:
- Map your patient journey: You need to write down each step from the first booking to the final payment, and who on your team owns it. Dr. Jonathan Spages, who runs a functional medicine practice in Florida, recommends doing so. He says, “The technology should support that process rather than forcing the practice to completely change how it provides care.”
- Rule out vendors who don’t have the right certifications: Confirm the product appears on ONC’s Certified Health IT Product List and that the vendor will sign a business associate agreement (BAA). If the answer is no, find another vendor instead.
- Make vendors demo your hardest workflow: What’s the most important task or documentation in your workflow? For example, a behavioral health practice might prioritize interoperability or shared access internally as patients move from a psychologist to a psychiatrist that prescribes medication. Make sure the vendor shows how the EHR works with different systems in your tech stack.
- Keep your tools under one login: Ideally, your EHR should have multiple modules so that you can consolidate your tech stack as much as possible. In fact, 63% of providers say they prefer one login and unified tools when asked how AI should integrate with their EHR. The same principle applies to other clinical or administrative modules.
- Understand the total cost of ownership: The cost of an EHR is just the direct cost. You also need to consider additional factors like implementation, data migration, staff training, additional integrations, and maintenance (for on-premise EHRs). Practice owners like Dr. Rokhsar also recommend expecting a temporary dip in patient volume during the initial weeks since it takes time for your staff and patients to ramp up.
- Ask about data ownership: Ask what format your data comes out in and whether the data export actually costs extra. This is critical because you should own your data, especially if you decide to migrate between EHRs.
- Get the SLAs and uptime documented: Choose a vendor that commits to high uptime in its service level agreement (SLA) and has few or no outages on record. Even a 10-minute outage can shut your practice down completely.
- Run a pilot with your staff: Run a demo first with your front desk lead and billing staff to see whether the EHR fits your current workflows. After that, run a 30-day pilot with your staff to see how it works before committing to a long-term contract.
| When | What usually happens | What to do |
| Before go-live | Workflows and roles are still unclear | Decide who documents what, set up templates and billing codes, run a test patient from intake to billing, and write your downtime plan |
| Weeks 1 to 2 | The schedule is lighter, and the system looks fine | Keep the schedule light and name an in-house go-to person who logs the workarounds staff use |
| Weeks 2 to 6 | Full volume returns, notes go unfinished, templates don’t fit, and the first claim denials arrive | Review templates and workflows at the one-month mark, and check early denials for setup errors |
| Month 2 onward | Training fades, and old habits creep back | Block weekly admin time for the first two months and schedule a refresher after your first busy season |
A checklist to evaluate EHR vendors
Use this checklist to compare vendors side by side:
- Listed on ONC’s Certified Health IT Product List
- Signs a business associate agreement
- Offers role-based access controls and audit logs
- Handles the hardest workflow in your specialty during the demo
- Connects charting, scheduling, billing, and patient messaging under one login
- Integrates with your labs, imaging centers, pharmacies, and regional health information exchange
- Includes AI documentation you can review and edit before signing
- Commits to high uptime in a written SLA, with a clean outage history
- Spells out data export terms, including format and cost, in the contract
- Lists every cost upfront, including migration and training
- Provides onboarding and support hours that match your clinic schedule
- Shares references from practices in your specialty
Choose an EHR that keeps your practice connected
Ultimately, your EHR needs to fit how your practice runs without creating unnecessary manual burden for your team. Everything about your patients should live in each record, and that can only happen with a “connected care” system that gets the job done.
That’s the idea behind Tebra’s EHR.
It’s built for private practices, and the cloud-based, ONC-certified platform connects everything you need to help your patients. For instance:
If you’re curious about how to use ehr systems and see how Tebra’s connected EHR works, take our self-guided tour and explore the platform.
Frequently asked questions
- Confirm ONC certification and HIPAA compliance.
- Match the system to your specialties and daily workflows.
- Compare integrated billing and scheduling, plus transparent pricing.
- Request demos, then weigh training and support.

You might also be interested in
- EHR vs. EMR: What’s the Difference? — Understand the key distinctions so you can choose the right system for your practice.
- How EHRs and Healthcare Technology Improve Efficiency — Learn how modern EHR systems streamline workflows, save time, and reduce administrative overhead.
- Want to see an EHR in action? Book a Free Demo and experience how the right system can transform your practice!
- Current Version – Nov 02, 2026Written by: Tanaaz KhanChanges: This article was updated to include the most relevant and up-to-date information available.
- Sep 12, 2025Written by: Jean LeeChanges: This article was updated to include the most relevant and up-to-date information available.
- Aug 18, 2025Written by: Jean LeeChanges: This article was updated to include the most relevant and up-to-date information available.
- Feb 21, 2025Written by: Becky WhittakerChanges: This article was updated to include the most relevant and up-to-date information available.



Subscribe to The Intake: A weekly check-up for your independent practice




